Core Modalities in Depression Therapy for Professionals

Depression therapy for professionals is a structured, evidence-based treatment approach that adapts psychotherapeutic modalities—such as Cognitive Behavioral Therapy (CBT), Behavioral Activation (BA), and Interpersonal Psychotherapy (IPT)—to the cognitive demands and executive function challenges of high-pressure careers. It targets the neural and behavioral patterns that underlie depressive episodes, helping high-performing leaders, healthcare workers, attorneys, and corporate executives regain motivation, decision-making capacity, and emotional resilience. When clinical depression alters neural pathways, diminishes executive function, and strips away motivation, standard advice like "take a vacation" falls flat. Navigating out of this state requires rigorous, evidence-based psychotherapies tailored to the cognitive demands of high-pressure careers.
The American Psychological Association (APA) Clinical Practice Guideline recommends seven primary psychotherapy interventions for adult depression alongside second-generation antidepressants. In our virtual clinical practice, we deliver these evidence-based frameworks via tailored individual therapy, allowing clients to target cognitive fatigue and emotional exhaustion without leaving their offices.
| Psychotherapeutic Modality | Typical Session Count | Primary Clinical Mechanism | Best Suited For |
|---|---|---|---|
| Cognitive Behavioral Therapy (CBT) | 6–20 weekly sessions | Modifying cognitive distortions and core schemas; behavioral experiments | Rumination, perfectionism, performance anxiety |
| Behavioral Activation (BA) | 12–24 weekly sessions | Systematically increasing positive reinforcement and breaking avoidance cycles | Deep apathy, lethargy, career inertia |
| Cognitive Therapy (CT) | 8–28 weekly sessions | Socratic dialogue to restructure underlying maladaptive beliefs | Impostor syndrome, harsh self-criticism |
| Interpersonal Psychotherapy (IPT) | 8–20 weekly sessions | Resolving role disputes, role transitions, and interpersonal deficits | Executive transitions, workplace conflict, isolation |
| Mindfulness-Based Cognitive Therapy (MBCT) | 8 weekly sessions (group/individual) + retreat | Decentering from depressive thoughts via non-judgmental present awareness | Relapse prevention, high somatic stress |
| Short-Term Psychodynamic Therapy | 8–20 weekly sessions | Resolving unconscious conflicts and maladaptive defense mechanisms | Chronic relational patterns, burnout tied to early identity |
| Supportive Therapy | 4–20 bi-weekly sessions | Therapeutic alliance, emotional stabilization, and ego strengthening | Acute crises, adjustment reactions |
Cognitive and Behavioral Interventions
Cognitive and behavioral approaches form the backbone of modern clinical care. Cognitive Behavioral Therapy (CBT) operates on the principle that our interpretations of events—rather than the events themselves—drive our emotional and physiological reactions. In corporate and clinical settings, cognitive distortions often manifest as all-or-nothing thinking ("If this project fails, my entire career is ruined") or catastrophizing. Through Socratic questioning and structured thought records, clinicians help professionals identify, stress-test, and reconstruct these automatic thoughts.
Behavioral Activation (BA) tackles the physical and emotional inertia of depression. When depression sets in, professionals often withdraw from rewarding activities to conserve energy, inadvertently cutting off all sources of positive environmental reinforcement. BA systematically schedules mastery- and pleasure-based activities, re-engaging the brain's reward pathways.
For time-strapped professionals, brief and targeted adaptations yield remarkable results. For instance, an evaluation of SHAPE cognitive therapy coaching for PTSD and depression symptoms in healthcare workers demonstrated that brief, 20- to 40-minute coaching calls using trigger discrimination and IF-THEN planning dramatically improved clinical outcomes. In that cohort, reliable recovery rates for depression jumped from 15.8% during baseline monitoring to 64.3% post-intervention, with 51.5% of participants having had no prior mental health treatment.
Interpersonal, Psychodynamic, and Mindfulness Approaches
Career paralysis rarely happens in a vacuum. It frequently emerges during major workplace upheavals, structural reorganizations, or toxic team dynamics. Interpersonal Psychotherapy (IPT) focuses directly on these social and occupational contexts, classifying distress into four domains: role transitions (e.g., stepping into a high-stakes leadership role), role disputes (e.g., irreconcilable conflicts with a board or partner), grief, and interpersonal sensitivity. By clarifying expectations and improving communication strategies, IPT restores professional agency. When workplace strain spills over into domestic life, integrating family therapy helps repair relational dynamics and establishes a grounded home support system.
Short-term psychodynamic therapy explores how early life adaptations and internalized expectations drive current professional behaviors. High achievers frequently develop an unconscious defense mechanism where personal self-worth is entirely contingent on flawless output. When setbacks occur, this defense collapses into severe depressive paralysis.
Complementing these modalities, Mindfulness-Based Cognitive Therapy (MBCT) blends standard cognitive exercises with mindfulness meditation. MBCT teaches professionals to observe negative affective states as passing mental events rather than absolute truths, preventing transient work stress from escalating into full-blown depressive relapse.
Tailoring Depression Treatment by Severity and Clinical Need
Depression exists along a spectrum from mild distress to severe, disabling illness. Effective care requires a stepped-care model that adjusts clinical intensity to the patient's presentation, psychiatric history, and DSM-5 specifiers (such as anxious distress, mixed features, or melancholic features).
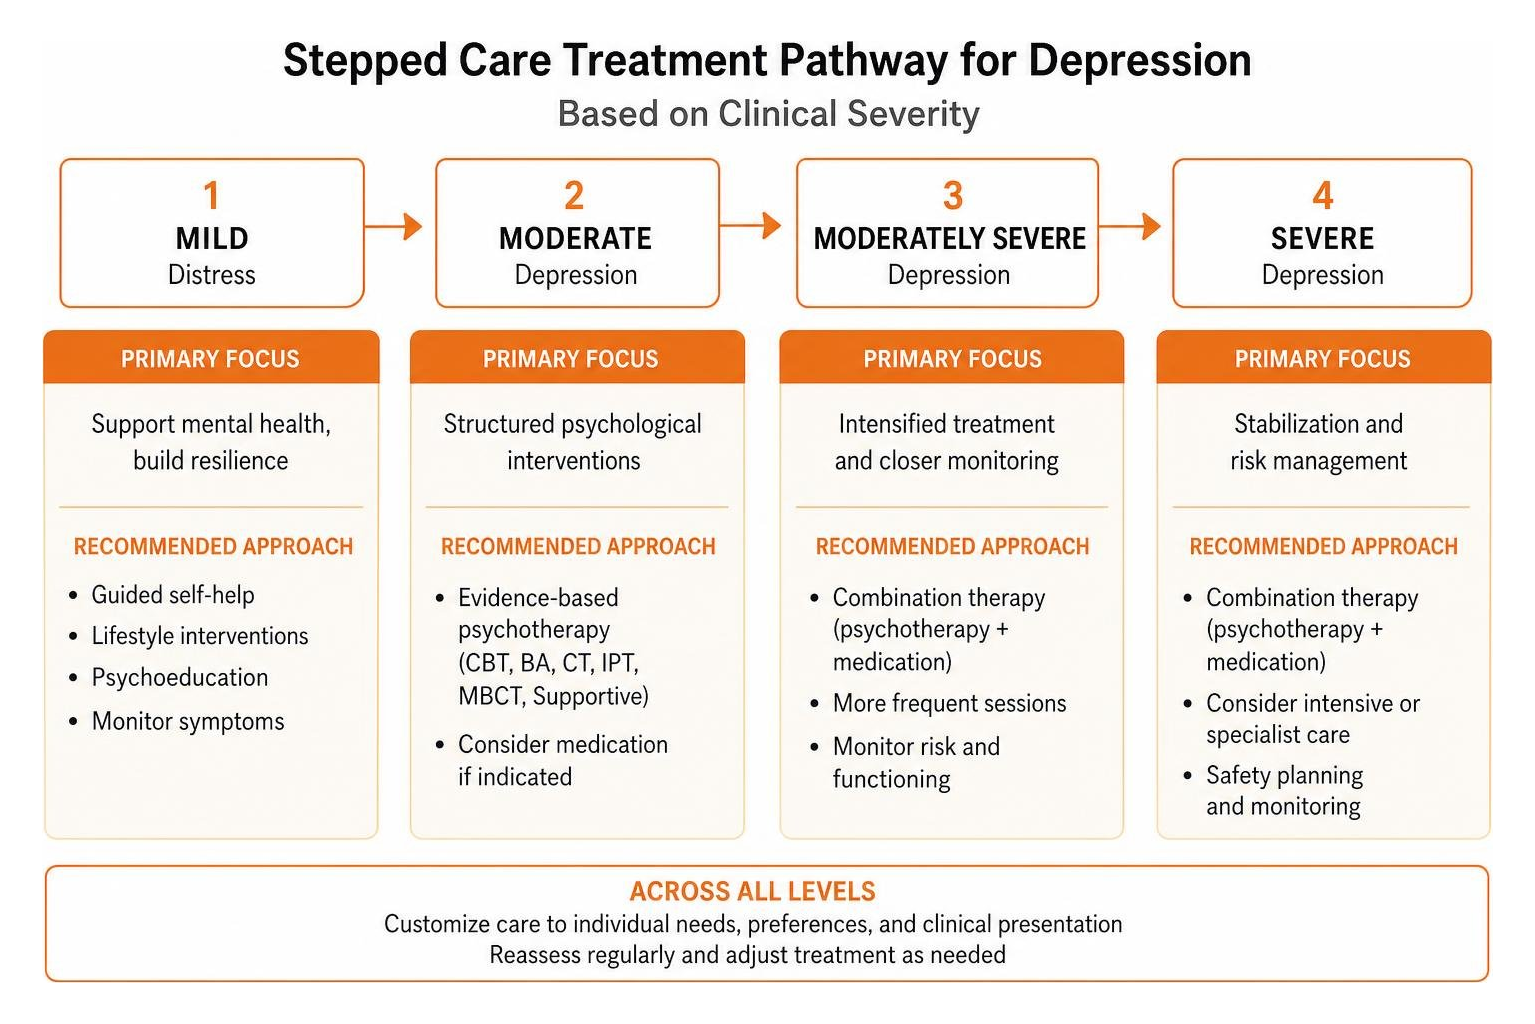
A pivotal study on the moderating effect of psychological well-being on burnout and depressive symptoms revealed an important dynamic: high psychological well-being can sometimes amplify the emotional contrast felt when burnout strikes, leaving high-functioning individuals unexpectedly vulnerable to sharp depressive crashes. A structured, tiered approach ensures interventions match the true depth of clinical need.
Mild Depression: Guided Self-Help, Lifestyle, and Complementary Interventions
For mild depressive episodes, formal psychotherapy or pharmacotherapy may not be immediately necessary. Clinicians often recommend a period of watchful waiting paired with active lifestyle interventions:
- Guided Self-Help: Completing 6–8 structured, CBT-based modules or workbooks supported by brief clinical check-ins.
- Cardiovascular and Resistance Exercise: Engaging in 150 minutes of moderate aerobic exercise weekly, which stimulates brain-derived neurotrophic factor (BDNF) synthesis and rivals mild antidepressant monotherapy.
- Sleep Hygiene Protocols: Anchoring circadian rhythms by maintaining strict wake times and eliminating blue-light exposure 60 minutes before sleep.
- Nutritional Psychiatry: Adopting anti-inflammatory, Mediterranean-style dietary patterns rich in omega-3 fatty acids.
- Herbal Supplements with Caution: While St. John's wort demonstrates efficacy in mild depressive states, clinicians strongly caution against unmonitored use due to its potent induction of cytochrome P450 enzymes, which dangerously lowers the blood levels of oral contraceptives, anticoagulants, and immunosuppressants.
Moderate to Severe Depression: Combination Protocols and Pharmacotherapy
When depression progresses to moderate or severe stages—marked by pervasive anhedonia, executive dysfunction, and marked functional impairment—combination therapy (antidepressants plus psychotherapy) becomes the gold standard. Empirical research shows that pairing second-generation antidepressants with CBT produces higher response and remission rates than either modality alone.
Medications help restore synaptic concentrations of serotonin, norepinephrine, and dopamine, effectively lifting the heavy neurochemical fog and restoring the cognitive capacity needed to engage in psychotherapy.
| Medication Class | Generic (Brand) | Standard Dosing Range | Mechanism of Action | Common Side Effects & Clinical Notes |
|---|---|---|---|---|
| SSRI | Sertraline (Zoloft) | 50–200 mg daily | Selective Serotonin Reuptake Inhibition | Nausea, insomnia, sexual dysfunction, headache. Excellent safety profile. |
| SSRI | Fluoxetine (Prozac) | 10–80 mg daily | Selective Serotonin Reuptake Inhibition + 5-HT2C antagonism | Activating; long half-life minimizes abrupt withdrawal symptoms. |
| SSRI | Citalopram (Celexa) | 20–40 mg daily | Selective Serotonin Reuptake Inhibition | Dose capped at 40 mg (20 mg in older adults) due to QT-prolongation risks. |
| SNRI | Venlafaxine (Effexor XR) | 75–300 mg daily | Serotonin & Norepinephrine Reuptake Inhibition | Nausea, dry mouth, dose-dependent blood pressure elevations. |
| NDRI | Bupropion (Wellbutrin XL) | 150–450 mg daily | Norepinephrine & Dopamine Reuptake Inhibition | Activating, no sexual side effects, aids focus; contraindicated in seizure/eating disorders. |
Advanced Strategies for Treatment-Resistant Depression
Approximately one-third of individuals with major depressive disorder do not achieve remission after two adequate trials of first-line antidepressants. For these treatment-resistant cases, advanced psychiatric interventions are required:
- Pharmacological Augmentation: Adding lithium carbonate (targeting a serum level of 0.6–0.8 mEq/L, with renal and thyroid monitoring every 3–6 months) or atypical antipsychotics (such as aripiprazole 2–10 mg daily or quetiapine 150–300 mg daily).
- Repetitive Transcranial Magnetic Stimulation (rTMS): A non-invasive outpatient procedure that uses focused magnetic pulses to stimulate the left dorsolateral prefrontal cortex, with zero cognitive downtime for working professionals.
- Esketamine (Spravato): An NMDA receptor antagonist nasal spray administered in certified clinical settings for rapid symptom reduction.
- Electroconvulsive Therapy (ECT) and Vagus Nerve Stimulation (VNS): Highly effective neuromodulation strategies reserved for severe, life-threatening, or profoundly intractable depression.
Step-by-Step Clinical Management, Safety, and Medication Protocols
Delivering effective depression therapy for professionals requires rigorous medical oversight, consistent safety checks, and continuous outcome tracking. High-achieving individuals often mask their symptoms behind polished workplace personas, making systematic clinical assessment crucial.

A poignant discussion on high-functioning depression among clinicians emphasizes that professionals frequently maintain exceptional outward productivity while quietly experiencing profound emotional exhaustion. Clinicians must balance respect for professional autonomy with proactive safety monitoring.
Initiating Pharmacotherapy, Monitoring, and Addressing Special Populations
When initiating an antidepressant, patient monitoring must be frequent and structured:
- Initial Monitoring Cadence: Patients should be evaluated every 1–2 weeks during the first 4 weeks to assess tolerability, calibrate dosing, and track therapeutic response.
- FDA Black Box Warning Vigilance: Clinicians and patients must closely track emergent agitation, anxiety, or suicidal ideation—particularly in individuals under 25 years old—during the first few weeks of treatment or following dose adjustments.
- Consolidation and Maintenance: Clinical improvements typically emerge within 2 to 4 weeks. Once full symptom remission is achieved, the therapeutic dose should be maintained for at least 4 to 6 months (and up to 2 years for recurrent episodes) to prevent relapse.
Special Population Considerations:
- Perinatal and Breastfeeding Professionals: Treatment decisions require balancing the risks of untreated maternal depression against minimal medication exposure. Sertraline remains a preferred first-line choice due to low placental transfer and minimal excretion into breast milk.
- Young Professionals (<25 Years): Close weekly monitoring is mandatory during the initial titration window to evaluate behavioral activation and paradoxical mood swings.
- Comorbid Medical Conditions: Prescribers must evaluate hepatic and renal clearance pathways and screen for drug-drug interactions, particularly in patients managing cardiovascular disease or metabolic disorders.
Discontinuation Protocols and Safe Antidepressant Tapering
Antidepressants are not addictive, but abruptly stopping them can trigger Antidepressant Discontinuation Syndrome (ADS). Symptoms include flu-like malaise, insomnia, nausea, hyperarousal, and sensory disturbances ("brain zaps"), typically lasting 1 to 2 weeks.
Clinicians must carefully differentiate discontinuation symptoms from true depressive relapse. Relapse develops gradually over several weeks and involves pervasive cognitive symptoms (guilt, anhedonia, hopelessness), whereas discontinuation syndrome emerges within 24 to 72 hours of dose reduction and is predominantly physical. All tapering should follow a hyperbolic, stepwise schedule over several months alongside a personalized relapse-prevention plan.
Implementing Depression Therapy for Professionals in High-Pressure Workplaces
High-performance workplace cultures frequently normalize overwork, emotional containment, and constant availability. Over time, this environment erodes mental health and leads to career paralysis.
A comprehensive systematic review and meta-analysis of interventions to reduce or prevent symptoms of common mental disorders and suicidality in physicians found that skill-based interventions—such as CBT and structured stress management—significantly reduce psychiatric symptoms across demanding professional groups, with treatment benefits lasting up to 12 months. Finding insightful perspectives on modern workplace wellness through our telehealth blog resources helps executives stay informed about evidence-based mental health strategies.
Integrating Shared Decision-Making into Depression Therapy for Professionals
Successful therapy for executives, physicians, and attorneys relies on collaborative decision-making:
- Autonomy Preservation: High-functioning individuals respond best when treated as active partners in their care. Clinicians present evidence-based options, and together they select the treatment path that aligns with the client's values and schedule.
- Biopsychosocial Framing: Presenting depression as a manageable medical and psychological condition reduces self-stigma, reframing care as an essential investment in cognitive and emotional performance.
- Outcome Tracking: Utilizing standardized metrics (such as the PHQ-9 and GAD-7) every two to four weeks provides clear, objective data on recovery progress.
Flexible Modalities and Workplace Integration
Busy professionals rarely have two hours to spare for midday clinic commutes. Modern teletherapy models bridge this gap with flexible, accessible care:
- HIPAA-Compliant Virtual Visits: High-definition, encrypted video sessions allow professionals to attend therapy from a private office or home workspace.
- Targeted Micro-Sessions: Combining 30-minute cognitive coaching sessions with self-paced digital learning modules allows clients to build resilience skills without disrupting their working hours.
- Strategic Boundary Setting: Therapy helps professionals establish firm working boundaries—such as designated offline hours and protected focus time—shielding them from chronic burnout.
Frequently Asked Questions About Depression Therapy for Professionals
Navigating clinical care while managing a demanding career brings up understandable questions regarding privacy, timelines, and treatment options. If you have additional inquiries, explore our complete list of frequently asked questions.
How Long Does Depression Therapy for Professionals Usually Take?
A standard course of evidence-based psychotherapy (such as CBT or IPT) typically spans 8 to 20 weekly sessions. Many professionals experience noticeable symptom relief within the first 4 to 6 weeks. Following initial recovery, monthly booster sessions are often recommended for 3 to 6 months to reinforce new cognitive patterns and prevent relapse.
When Should Medication Be Added to Psychotherapy for Career Burnout?
Medication is indicated when depressive symptoms reach a moderate-to-severe threshold, when severe rumination impairs day-to-day decision-making, or when psychological therapy alone has not yielded sufficient progress after 6 to 8 weeks. A psychiatric evaluation helps determine whether an antidepressant can provide the neurochemical support needed to re-engage with therapy and work.
How Does Telehealth Protect Confidentiality for High-Profile Professionals?
All Points North Telehealth Therapy operates in full compliance with federal HIPAA privacy regulations. Our virtual platform utilizes end-to-end bank-grade encryption, discreet electronic scheduling, and secure medical records systems. This ensures your care remains completely confidential, protecting your professional standing and personal privacy.
Conclusion
Career paralysis is not an insurmountable roadblock or a personal failure; it is a clear clinical signal that your mind and body need support. High-pressure careers demand exceptional mental clarity, and attempting to push through clinical depression with willpower alone only deepens exhaustion and delays healing.
By combining evidence-based psychotherapy, precision medical management, and flexible virtual delivery, you can dismantle depressive inertia, restore cognitive resilience, and build sustainable work patterns. At All Points North Telehealth Therapy, our master's- and doctoral-level clinicians specialize in helping high-performing leaders reclaim their health and momentum.
Explore our specialized professional program today to schedule a confidential consultation and take the first step toward lasting recovery.